Liver Resection (Hepatectomy): What to Expect Before, During, and After Surgery
Learn how liver resection is planned and performed, including its role in treating secondary liver cancers such as colorectal liver metastases.
Read More
Colorectal cancer surgery removes cancerous growths from the colon, rectum or anus while preserving bowel function and quality of life wherever possible. It is the main curative treatment for colon cancer and rectal cancer, and the exact operation depends on the tumour's location, stage and the patient's health. Reaching an experienced colorectal cancer surgeon in Delhi early gives the best chance of a cure and of avoiding a permanent stoma.
At Liver Surgeons, Dr. Ashish George offers the full range of colon cancer treatment and colorectal cancer treatment: curative surgery for localised tumours, laparoscopic and robotic minimally invasive surgery, sphincter-preserving techniques to avoid a permanent ostomy, and genetic counselling for hereditary conditions such as Lynch syndrome. This page is part of our wider cancer surgery programme .




Specialist diagnosis, minimally invasive surgery, sphincter-preserving treatment and multidisciplinary colorectal cancer care in Delhi.
Colon and rectal cancer often develop from polyps over years, and early disease may cause no symptoms, which is why screening matters. Warning signs to act on include:
Colon cancer diagnosis is confirmed and staged with:
The right colon surgery or rectal operation depends on where the tumour is. The table below covers the procedures performed at our Delhi centre, including the full range of types of advanced surgery for colon cancer.
| Procedure | When It Is Used | Procedure Details |
|---|---|---|
| Partial Colectomy (Hemicolectomy) | Tumours confined to one part of the colon | The colon removal operation for most colon cancers; the healthy ends are rejoined |
| Total Colectomy | Widespread tumours or Lynch syndrome | Removes the whole colon and may require an ileostomy |
| Low Anterior Resection (LAR) | Rectal tumours where the sphincter can be preserved | Removes the tumour and rejoins the bowel; a temporary stoma is sometimes used |
| Laparoscopic or Robotic Colectomy | Early-stage cancers and suitable tumours | Smaller incisions, less pain and faster recovery of approximately 2 to 4 weeks |
| Sphincter-Preserving Surgery (TAMIS or Intersphincteric Resection) | Low rectal tumours | Avoids a permanent stoma in selected ultra-low rectal cancers |
| Abdominoperineal Resection (APR) | Very low rectal or anal tumours involving the sphincter | Requires a permanent colostomy and is used only when the sphincter cannot be saved |
Laparoscopic surgery for colon cancer and laparoscopic surgery for colorectal cancer use several small incisions and a camera-guided approach instead of one large open cut.
For suitable tumours, the advantages over open surgery are clear: less pain, lower infection and wound complication risk, faster recovery of approximately 2 to 4 weeks rather than 6 to 8 weeks, and a better cosmetic result, with the same oncological, or cancer-clearing, outcome in experienced hands.
Robotic surgery extends these advantages to complex rectal cases where precision in the pelvis matters most. Not every tumour suits a keyhole approach, and the honest judgement of when open surgery is safer is part of what defines a specialist.
Surgery is often only part of the treatment. Chemotherapy for colon cancer is commonly given after surgery, known as adjuvant chemotherapy, for stage 3 and some stage 2 tumours to reduce the risk of recurrence.
For rectal cancer, chemotherapy before surgery, also known as neoadjuvant chemoradiation, is frequently used to shrink the tumour, make sphincter-preserving surgery more likely, and lower the chance of the cancer coming back.
At our Delhi centre, the sequence of chemotherapy, radiation and curative surgery for colorectal cancer is planned jointly with medical and radiation oncology at a tumour board, so every element works together.
Patients researching recent advances in colon cancer surgery and advanced surgery for colorectal cancer treatment will find the following modern techniques available at our Delhi centre:
Some colorectal cancers are hereditary, most commonly due to Lynch syndrome, which raises the lifetime risk of colon and other cancers.
Our Delhi centre offers genetic counselling and MSI/MMR testing, risk-reducing or prophylactic surgery for confirmed high-risk carriers, and lifelong surveillance with colonoscopy every 1 to 2 years.
Managing hereditary risk well can prevent cancer altogether or detect it at its most curable stage.
Our Delhi centre uses ERAS protocols, so most laparoscopic patients are discharged in 3 to 5 days. Recovery to normal activity takes approximately 2 to 4 weeks after minimally invasive surgery and 6 to 8 weeks after open surgery.
The colon cancer surgery cost depends on the operation, including partial or total colectomy, LAR, sphincter-preserving or robotic surgery, the length of hospital stay, and whether chemotherapy or radiation is needed alongside surgery.
Because every case is different, an exact quote is only meaningful after staging.
Our Delhi team provides a clear, itemised and all-inclusive estimate before any commitment, with no hidden charges. As a general guide, costs here are typically 60 to 75 percent lower than equivalent treatment in the United Kingdom, United States or Australia.
Contact the team for a personalised estimate based on your reports.
Colorectal cancer surgery, and low rectal surgery in particular, is technically demanding. Outcomes and stoma-avoidance rates are strongly tied to the surgeon's experience.
When choosing a colorectal cancer doctor in Delhi, or searching for the best surgeon for colon cancer in Delhi or the best doctor for colorectal cancer in Delhi, consider:
Dr. Ashish George is among the leading colorectal cancer surgeons in the region, with more than 15 years of surgical oncology experience, 300 or more colectomies and sphincter-preserving surgeries, and expertise in laparoscopic and robotic colorectal surgery.
Patients searching for a colon cancer surgeon in Delhi, a colon specialist in Delhi, or the best doctor for colorectal cancer are referred to his team from across India and abroad.
As a high-volume colon cancer hospital in Delhi and colorectal cancer hospital in Delhi, Fortis Shalimar Bagh combines robotic surgery, 3D pelvic MRI planning, fluorescence imaging, ERAS protocols, a full multidisciplinary tumour board, and dedicated ostomy nursing. Patients receive world-class care at costs far below Western equivalents.
Delhi is one of Asia's established destinations for colorectal cancer surgery, combining high case volume with costs typically 60 to 75 percent lower than comparable procedures in the United Kingdom, United States or Australia.
For patients travelling to Dr. George's practice, support includes:
Whether you have a new diagnosis, a low rectal tumour where you want to avoid a permanent stoma, or hereditary risk needing genetic advice, our Delhi team offers the full range of colorectal cancer treatment from a single specialist backed by a full tumour board.Book a consultation with Dr. Ashish George at Fortis Hospital, Shalimar Bagh.
Most patients resume normal activities in 2 to 4 weeks, with full recovery by about 6 weeks. ERAS protocols at our Delhi centre allow discharge in 3 to 5 days for many laparoscopic cases.
Usually not. Most patients keep normal bowel function, and where a stoma is needed it is often temporary and later reversed. A permanent colostomy is reserved for very low rectal or anal tumours where the sphincter cannot be saved. Sphincter-preserving techniques are prioritised.
Yes. For suitable tumours, laparoscopic colon surgery gives the same cancer-clearing outcome as open surgery, with faster recovery, less pain and lower infection risk. The right approach depends on the tumour, which is assessed before surgery.
Often yes. Chemotherapy after surgery is standard for stage 3 and some stage 2 colon cancers. For rectal cancer, chemo and radiation are frequently given before surgery to shrink the tumour and improve the chance of preserving the sphincter.
Lynch syndrome is a hereditary condition that increases the risk of colorectal and some other cancers. It is managed with genetic testing, risk-reducing surgery for confirmed carriers, and lifelong surveillance colonoscopy every 1 to 2 years.
The cost depends on the procedure, whether robotic technology is used, and the length of stay. Our Delhi team gives a clear, all-inclusive estimate after staging, with no hidden charges. Costs are typically 60 to 75 percent lower than in Western countries.
Yes. Modern pouching systems are discreet and leak-proof, skin-protection care prevents irritation, and dedicated ostomy nurses provide support. Most ostomy patients return to a full, normal life.
Expert guidance on colorectal cancer surgery, liver metastases, minimally invasive and robotic surgery, pre-operative testing, advanced cancer surgery and specialist surgical care.
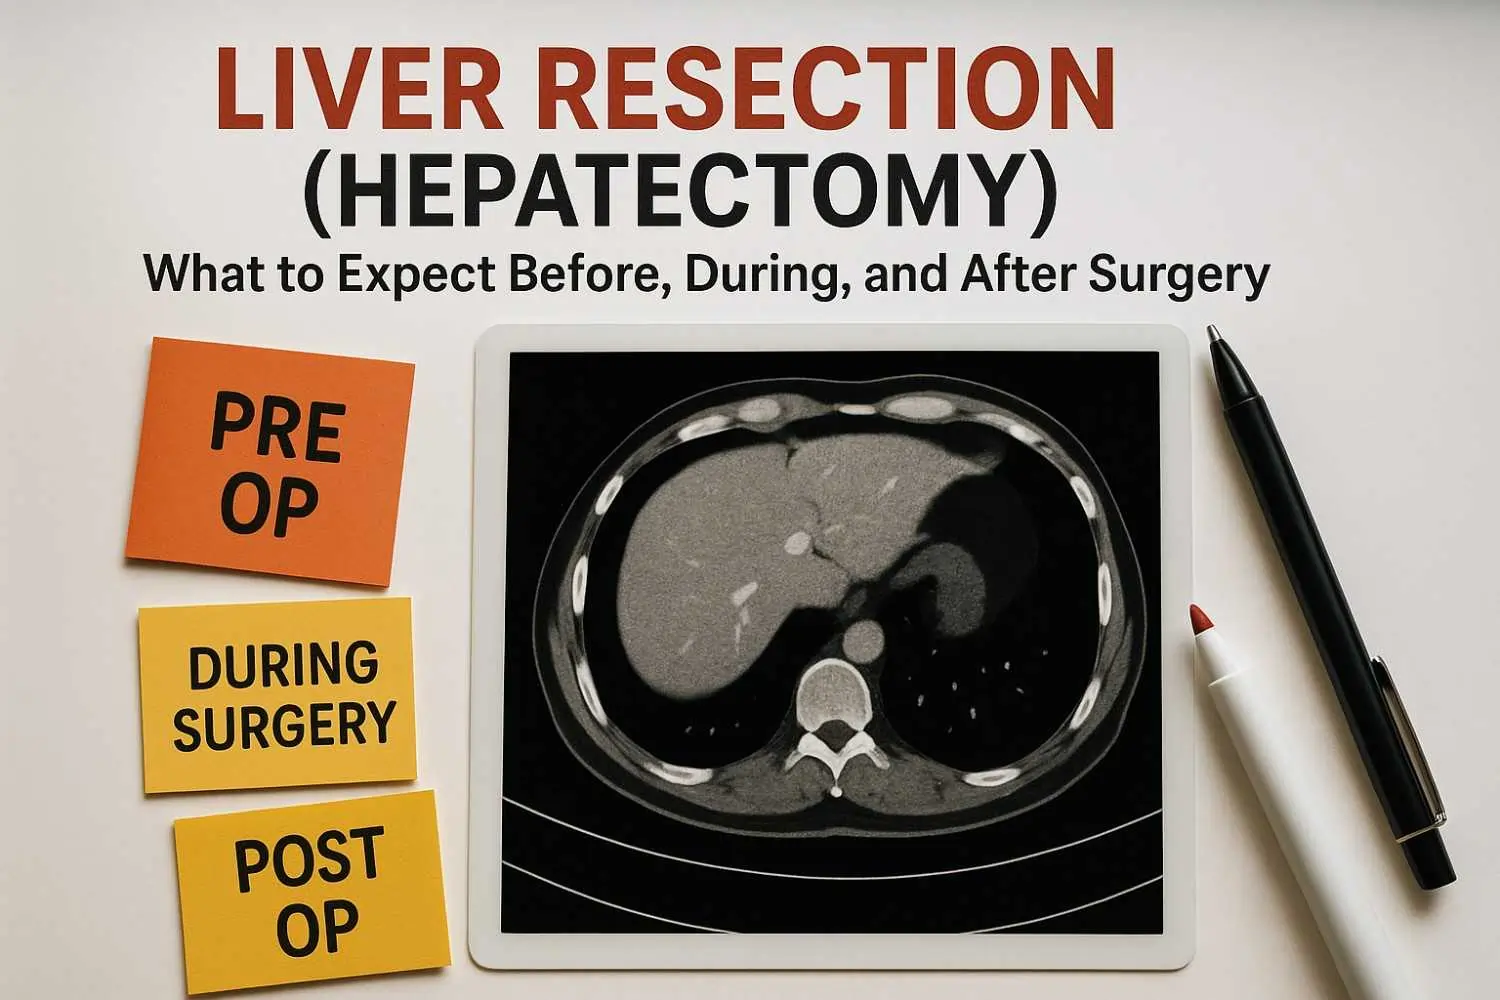
Learn how liver resection is planned and performed, including its role in treating secondary liver cancers such as colorectal liver metastases.
Read More
Explore advanced surgical treatment for liver, pancreas and biliary conditions, including surgery for colorectal cancer that has spread to the liver.
Read More
Compare robotic, laparoscopic and open surgical approaches, including differences in recovery, incision size and surgical precision.
Read More
Understand how robotic surgery can support complex cancer procedures with smaller incisions, greater precision and faster recovery.
Read More
Learn about CT, MRI, PET-CT, blood tests, staging and surgical fitness assessments used before complex cancer surgery.
Read More
Understand complex HPB surgery and how specialist liver surgery may become part of treatment when colorectal cancer spreads to the liver.
Read More
Learn what to consider when choosing an experienced specialist for complex cancer surgery, particularly when colorectal cancer involves the liver.
Read More
Understand how early cancer detection and accurate staging can preserve more treatment options and improve opportunities for curative surgery.
Read More