Liver Cancer Caught Early vs Late: Why Timing Changes Everything
Understand how early detection changes liver cancer treatment options, including resection, ablation, transplantation and long-term outcomes.
Read More
Liver cancer is one of the most serious and rapidly growing cancers in India. The most common type, hepatocellular carcinoma (HCC), develops in the liver cells themselves, most often in patients who already have chronic liver disease such as cirrhosis or chronic hepatitis B or C. Getting to an experienced liver cancer surgeon in Delhi early is what most improves the outlook, because the treatment that offers a cure, surgery or transplant, is only possible while the tumour is still confined to the liver.
The outlook for liver cancer has improved dramatically over the past decade, driven by better screening that detects tumours earlier and by advances in surgical technique, minimally invasive surgery, ablation technology and liver transplantation. Understanding early vs late liver cancer detection is crucial: when caught early, liver cancer is highly treatable and in many cases curable.
At Liver Surgeons, Dr. Ashish George offers the full spectrum of liver cancer treatment in Delhi, from surgical resection and tumour ablation to liver transplantation, all at a single specialist centre at Fortis Hospital, Shalimar Bagh. This page is part of our wider cancer surgery programme and advanced HPB surgery.




Specialist liver cancer care, including resection, ablation and liver transplantation
The liver is a common site for cancer spread from other organs, most often the colon and rectum. Surgical resection of liver metastases, particularly from colorectal cancer, is well established and can significantly extend survival and in some cases achieve cure.
Understanding your risk factors is the first step toward early detection, and early detection saves lives. The following significantly increase the risk of developing hepatocellular carcinoma:
Screening: all patients with cirrhosis from any cause should receive a 6-monthly abdominal ultrasound and AFP (Alpha-Fetoprotein) blood test. Hepatitis B patients without cirrhosis may also need surveillance depending on viral load and family history.
Liver cancer often produces no symptoms in its early stages, which is why surveillance for high-risk patients is so critical. When symptoms do appear, they may include:
If you have known liver disease and notice any sudden change in your condition, see your liver specialist immediately, as these symptoms can indicate HCC.
Accurate diagnosis and staging decide the treatment. Our Delhi centre uses:
In many cases HCC can be diagnosed on characteristic imaging alone without a biopsy, which avoids the risk of tumour seeding. A biopsy is only done when imaging is inconclusive.
Treatment is highly individualised. The right approach depends on tumour size and number, vascular invasion, underlying liver function (BCLC stage) and overall health. Every patient is discussed by a multidisciplinary team before a plan is finalised. The table below summarises the main options.
| Treatment | Best For | Recovery / Notes |
|---|---|---|
| Surgical Resection (Hepatectomy) | Early-stage HCC with preserved liver function; single tumours without significant cirrhosis or portal hypertension | 7 to 14 days in hospital; 4 to 6 weeks to normal activity; aim is a clear R0 margin |
| Liver Transplantation | HCC within Milan or UCSF criteria; removes the cancer and cures the underlying cirrhosis | 5-year survival within Milan criteria is 70 to 75 percent |
| Tumour Ablation (RFA / Microwave) | Tumours 3 to 5 cm or smaller; patients unfit for surgery; bridge to transplant | 1 to 2 days in hospital; return to activity in 1 to 2 weeks; repeatable |
| Transarterial Chemoembolisation (TACE) | Intermediate HCC with multiple tumours not suitable for resection; bridge to transplant | Interventional radiology; can be repeated |
| Systemic Therapy | Advanced HCC with vascular invasion or spread beyond the liver | Targeted and immunotherapy agents, managed with oncology |
Surgical removal of the tumour-bearing portion of the liver is the treatment of choice for early-stage HCC with adequate liver reserve. Dr. George performs both anatomical resections (removing defined liver segments by blood supply) and non-anatomical resections, using open, laparoscopic and robotic-assisted techniques. For suitable tumours, a robotic cancer surgeon in Delhi can offer liver tumour surgery in Delhi with less pain and faster recovery. The liver's regenerative capacity means even major resections, removing up to 70 percent of the liver, are survivable when the remaining liver is healthy. For keyhole options, see our minimal access liver surgery page; for tumours involving major vessels, see advanced ante-situm and ex-situ resection.
Transplantation offers a unique advantage in HCC: it removes the cancer and cures the underlying cirrhosis at the same time, eliminating the diseased liver in which new tumours would otherwise develop. Milan criteria (a single tumour up to 5 cm or up to 3 tumours each up to 3 cm, with no vascular invasion or spread) define standard eligibility, and ablation or TACE can be used as a bridge while awaiting transplant. See our liver transplant page for detail.
Because most liver cancer arises in a liver that is already diseased, treating it well requires a surgeon who understands both the cancer and the underlying liver, and who can offer transplant as well as resection. When choosing a liver cancer doctor in Delhi, or searching for the best doctor for liver cancer surgery in Delhi or a liver cancer specialist in Delhi, consider:
Dr. Ashish George is a specialist liver transplant and HPB surgeon and one of the leading liver cancer specialists in Delhi. Because he is also a transplant surgeon, patients receive the full range of options for hepatocellular carcinoma treatment in Delhi under one team, from resection to transplant. Patients searching for a liver cancer hospital in Delhi or the best doctor for liver cancer surgery are referred to his team from across North India and abroad. As a high-volume liver cancer hospital, Fortis Shalimar Bagh combines a dedicated liver ICU, robotic and 3D planning technology, interventional radiology for ablation and TACE, and a full transplant programme. Patients receive world-class hepatocellular carcinoma surgery in Delhi at costs substantially lower than in Western countries.
Delhi is one of Asia's established destinations for liver cancer surgery, combining high case volume with costs typically 60 to 75 percent lower than comparable procedures in the United Kingdom, United States, or Australia. For patients travelling to Dr. George's practice:
Full blood workup, AFP, imaging review, and assessment of underlying liver function.
BCLC staging to determine the most appropriate treatment.
Your case is reviewed by the liver surgeon, hepatologist, and radiologist to agree on the optimal treatment plan.
Surgical resection, ablation, TACE, or transplant evaluation — depending on your stage and liver function.
Surgical specimens are reviewed by specialist liver pathologists to confirm diagnosis, tumour grade, and margin clearance.
Dedicated liver ICU care post-surgery; outpatient management post-ablation.
Nutritional support and rehabilitation.
3-monthly imaging and AFP for the first 2 years post-treatment, then 6-monthly thereafter.
Vigilance for recurrence is essential.
Whether you have a new HCC diagnosis, a liver tumour that needs removal, or a referral for transplant assessment, our Delhi team offers the full range of liver cancer treatment in Delhi from a single specialist backed by a full transplant programme and tumour board.Book a consultation with Dr. Ashish George at Fortis Hospital, Shalimar Bagh.
Yes. When detected early (BCLC stage 0 or A), liver cancer is potentially curable through surgical resection or liver transplantation. The key is early detection through regular surveillance in high-risk patients.
For early-stage HCC treated with surgical resection, 5-year survival rates of 50 to 70 percent are achievable. Liver transplantation for HCC within Milan criteria offers 70 to 75 percent 5-year survival. Outcomes depend heavily on tumour stage, underlying liver function, and the expertise of the surgical team.
There is no single best treatment; the right one depends on your BCLC stage and liver function. Early tumours with good liver function are best treated by resection or transplant, small tumours by ablation, and intermediate disease by TACE. The advantage of a centre that offers all of these, including transplant, is that the treatment is matched to you rather than to what the centre happens to provide.
Surgical recovery involves discomfort that is managed effectively with pain medication. Minimally invasive laparoscopic or robotic techniques significantly reduce post-operative pain compared with open surgery, and recovery is faster.
Liver resection typically requires 7 to 14 days in hospital and 4 to 6 weeks before returning to normal activity. Minimally invasive resections allow faster recovery. Ablation procedures require only 1 to 2 days in hospital.
Yes. Advanced HCC can spread to the lungs, bones, lymph nodes and adrenal glands, which is why early detection and treatment before the cancer spreads is so important. Regular surveillance in high-risk patients is the best strategy.
Expert guidance on liver cancer detection, HCC diagnosis, HPB surgery, robotic liver surgery, liver cancer screening, transplant evaluation and liver transplant outcomes.
Understand how early detection changes liver cancer treatment options, including resection, ablation, transplantation and long-term outcomes.
Read More
Learn about AFP testing, liver function tests, CT, MRI and other investigations required before liver cancer and complex HPB surgery.
Read More
Learn how robotic HPB surgery can be used for selected liver and hepatobiliary tumours, including benefits, eligibility and recovery expectations.
Read More
Explore advanced surgical treatment for liver, pancreas, gallbladder and bile duct conditions, including liver tumours and complex cancers.
Read More
Understand when liver cancer may be treated with resection or advanced HPB surgery and when liver transplantation may be the better option.
Read More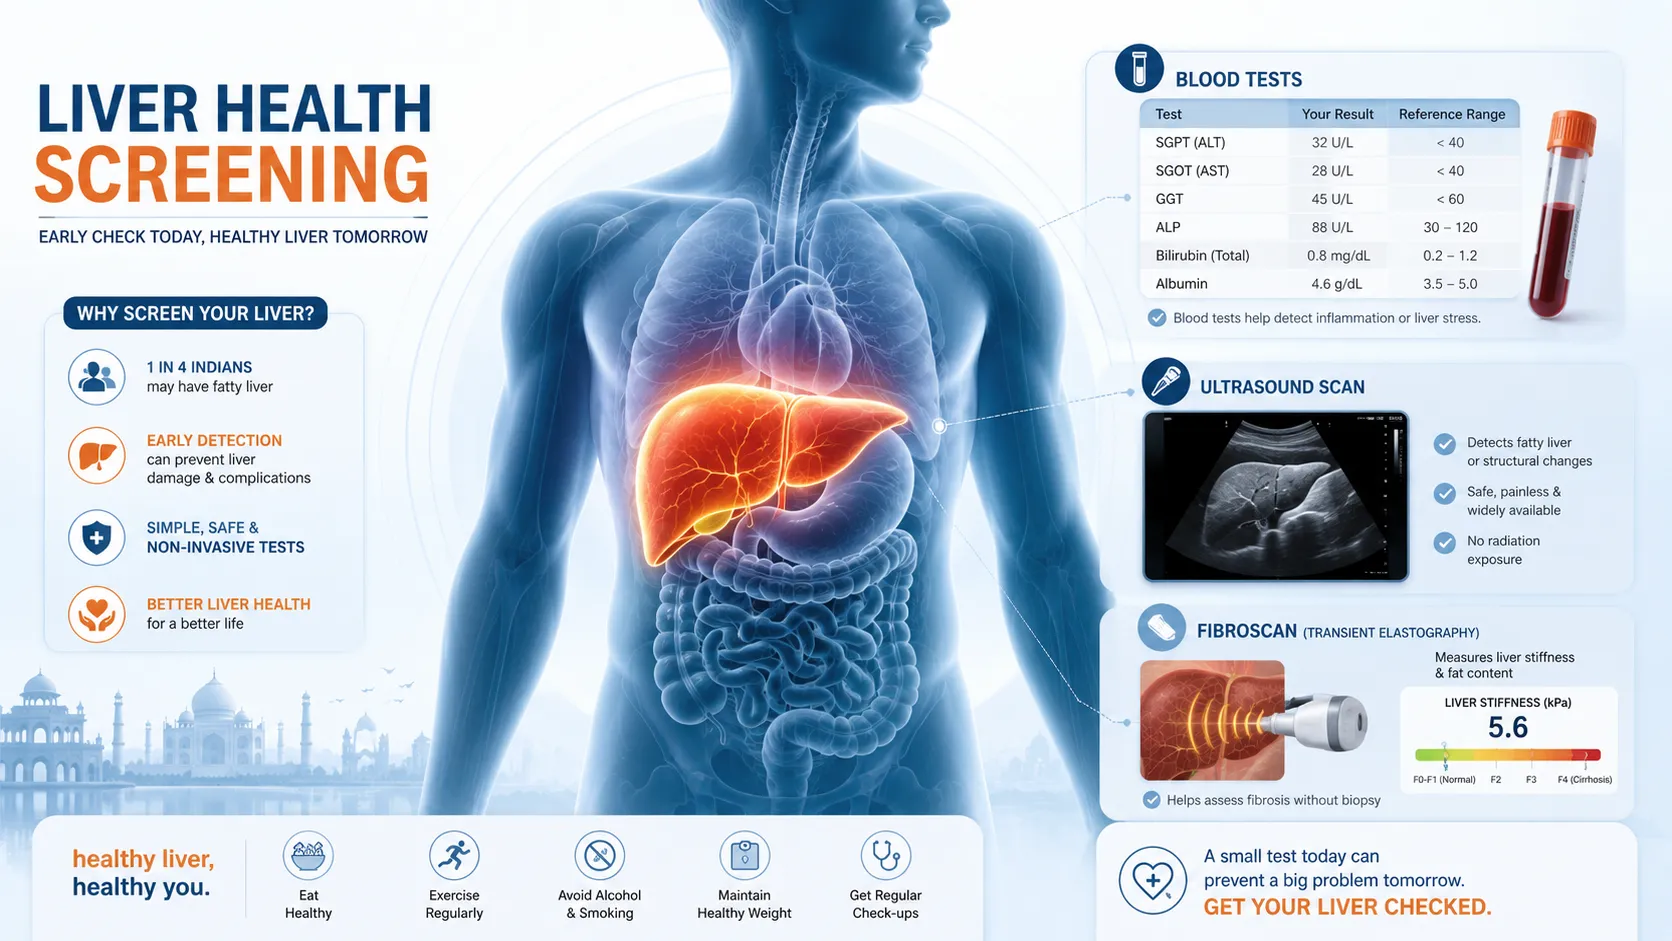
Learn how liver function tests, ultrasound, FibroScan and other screening tests help identify liver disease and cancer risk earlier.
Read More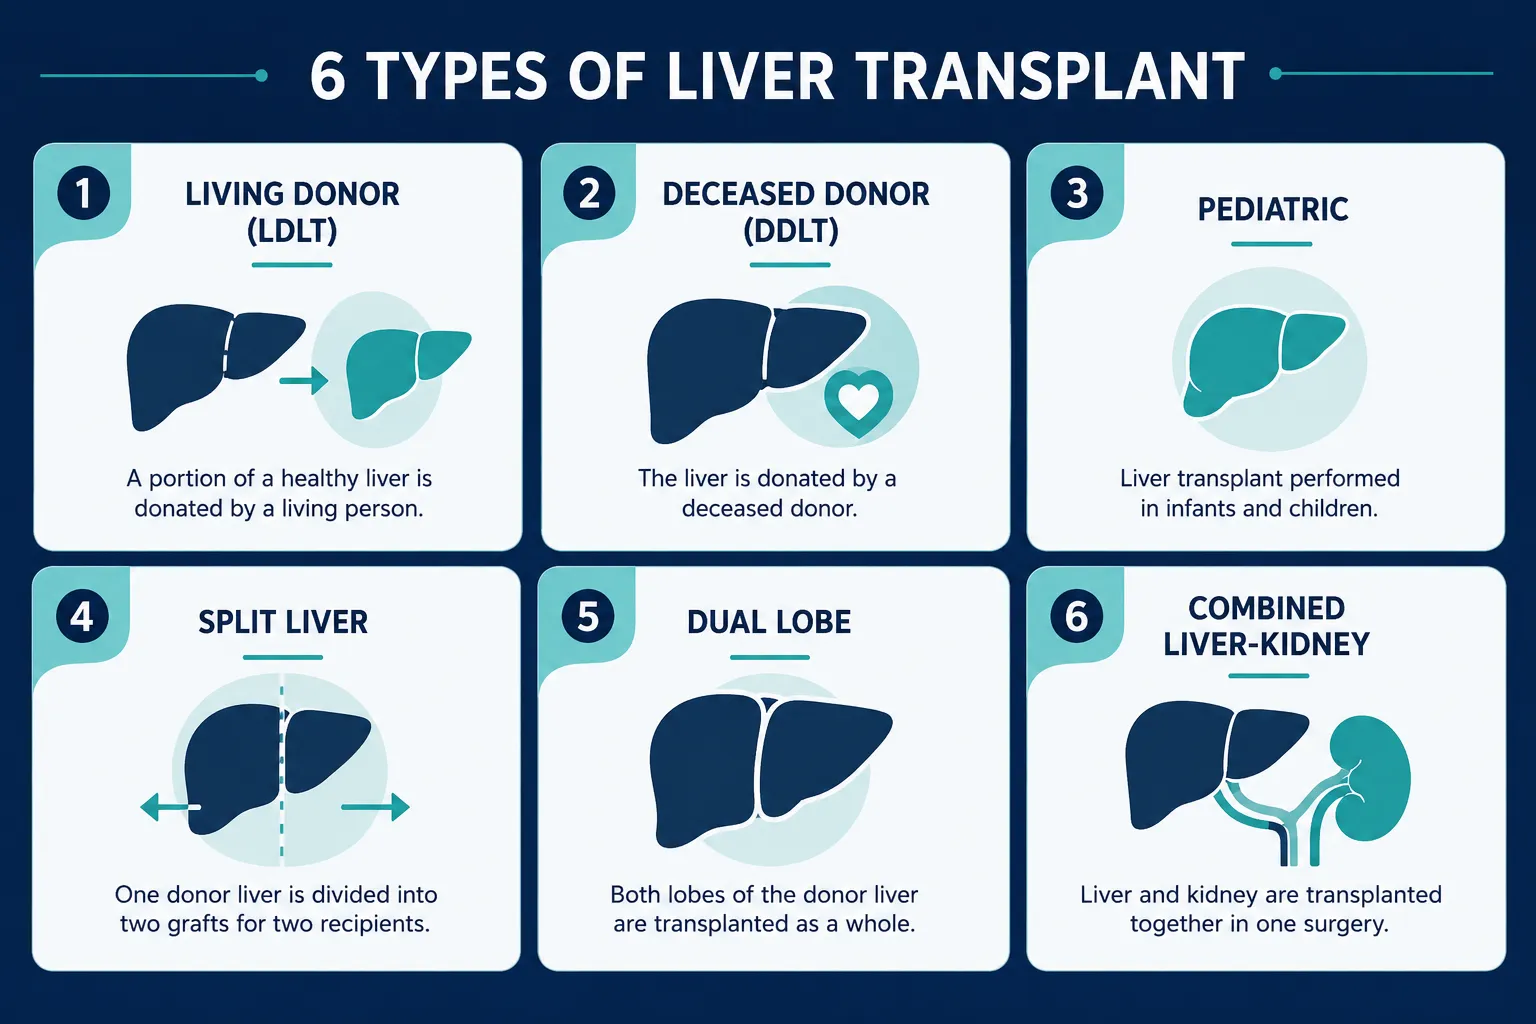
A complete guide to transplant eligibility, donor options, surgery, recovery and long-term care for advanced liver disease and selected HCC cases.
Read More
Understand patient survival, graft survival and the factors that influence liver transplant outcomes in India, including patients with advanced liver disease.
Read More